A routine dental cleaning, a scratched bug bite, or a minor skin infection usually is not just a cause for panic.
Your immune system typically quietens the threat before you even realize it is there.
In certain cases, those roaming bacteria slip past your defenses, enter your bloodstream, and manage to anchor themselves onto the inner lining of your heart chambers or valves.
Additionally, they trigger a fast-moving clinical emergency known as endocarditis.
This is not some standard or mild inflammation. Once these microbes take root, they build destructive cellular clumps. Consequently, they can quickly tear through delicate heart tissue or break off to cause sudden, life-threatening strokes.
Dealing with a condition this volatile means there is zero room for guesswork.
This guide untangles exactly how endocarditis operates, how doctors diagnose it today, who is most at risk, and the modern treatments keeping patients safe.
The Microscopic Sandbox: How Endocarditis Takes Hold
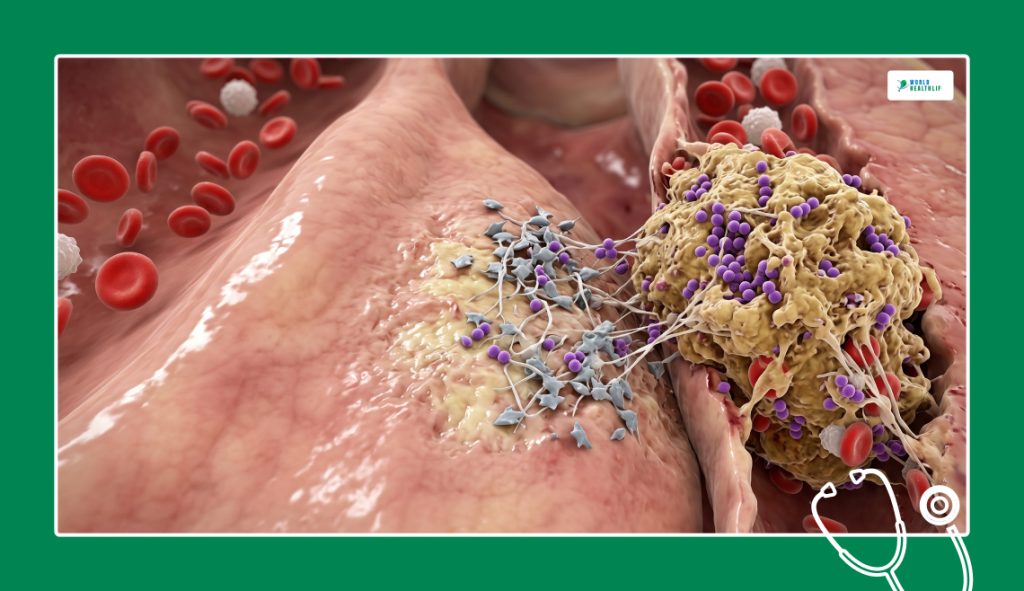
First, let us think of the endocardium. It is known as the smooth inner lining of your heart’s chambers and valves, just like a perfectly slick slide.
Under normal conditions, blood flows over it smoothly, and nothing can stick to it.
However, in case the lining gets nicked, roughened, or damaged by an underlying health issue, your body treats it like a cut.
Platelets and fibrin rush to the scene to patch it up, creating a rough, sticky surface. If bacteria or fungi happen to be floating in your blood at that exact moment, they use this rough patch as an anchor.
They bury themselves under layers of blood cells, multiplying into thick, slimy clusters called vegetations.
These vegetations act like physical roadblocks inside the heart, eating away at your valve flaps and constantly spraying infected debris into your main circulation.
Classifying The Threat: Infective Vs. Sterile Variants
Doctors divide this condition into separate categories on the basis of entirely on what is causing the cellular damage.
Infective Endocarditis (IE)
This is the most common version, happening when living, multiplying microbes physically invade the heart tissue.
The Acute Kind
This kind hits like a freight train out of nowhere. It can destroy a perfectly healthy heart valve in just a few days.
It is usually driven by aggressive strains like Staphylococcus aureus.
The Subacute Kind
In this kind, it plays a slow game.
It causes vague, flu-like symptoms over weeks or months, typically targeting valves that were already damaged or weak.
Milder oral germs like Viridans streptococci are usually to blame here.
The Fungal Kind
This kind is Rare but highly dangerous.
Strains like Candida form massive, stubborn clumps that standard medicines can’t touch.
These cases almost always require urgent open-heart surgery combined with heavy antifungal drugs.
Non-Infective Endocarditis
This variant involves no germs at all.
Instead, severe autoimmune conditions like lupus (SLE) or certain advanced cancers cause the body’s clotting system to go haywire.
The immune system mistakenly deposits completely sterile protein clumps onto the heart valves.
While there is no active infection to fight, these sterile clumps can still scar the valves or break free to cause sudden strokes.
Entry Points And Weak Spots: Who Is Most At Risk?
Germs generally struggle to damage a healthy heart.
An infection usually requires a direct entry pathway combined with a structural vulnerability.
| Risk Category | Specific Source | How Bacteria Take Advantage |
| Pathways Into Blood(How germs enter) | • Bleeding gums / dental work • Deep skin infections • Hospital IV lines | Microbes exploit raw tissue or invasive medical entry points to slip directly into circulation. |
| Structural Weaknesses(Where germs anchor) | • Congenital heart defects • Rheumatic fever scars • Age-related valve wear | Damaged tissue creates rough, turbulent surfaces that circulating bacteria can easily stick to. |
| Foreign Objects(Where germs hide) | • Artificial heart valves • Implanted pacemakers • Defibrillator wires | These devices lack a natural blood supply. Bacteria build a slimy biofilm layer over them to hide from the immune system. |
| Direct Injection(Direct blood access) | • Non-sterile needle use | Massive bacterial loads are introduced straight into the veins, primarily attacking the tricuspid valve on the right side of the heart. |
The Subtle Warning Signs: What to Look For
The condition often mimics a stubborn winter flu. Additionally, catching it early requires looking for a specific combination of whole-body warnings and vascular clues.
| Symptom Category | Specific Sign | What It Means Clinically |
| The Flu Illusion | Lingering fever, drenching night sweats, constant fatigue, unexplained weight loss | The body is locked in a prolonged inflammatory battle against a systemic internal infection. |
| Changing Murmurs | Brand-new heart murmur or an alteration of a pre-existing murmur | Microscopic bacteria are actively eroding a heart valve leaflet, forcing blood to leak backward. |
| Vascular Tell-Tales | Splinter nail hemorrhages, painless palm/sole Janeway lesions, tender finger/toe pad Osler’s nodes | Infected heart vegetation fragments have broken loose, causing localized micro-clots and immune reactions. |
The Diagnostic Blueprint: The 2023 Duke-ISCVID Strategy
A doctor cannot diagnose this condition with a quick look-over. Hospitals rely on the updated 2023 Duke-ISCVID Criteria to cross-reference multiple findings and officially classify a case as Definite, Possible, or Rejected.
| Criterion Type | Key Diagnostic Requirements |
| Major Indicators | • Positive Blood Cultures: Multiple separate blood draws taken hours apart growing identical, typical pathogens (e.g., S. aureus, E. faecalis). • Positive Imaging Evidence: Echocardiogram showing a shifting mass, new valve tear, or abscess. Includes advanced PET-CT and Cardiac CT scans for pacemakers/artificial valves. |
| Minor Indicators | • Predisposition: History of intravenous drug use or an implanted artificial heart valve/pacemaker. • Fever: Documented body temperature 38.0°C (100.4°F). • Vascular Phenomena: Blocked arteries, septic lung infarcts, or brain bleeds. • Immunological / Lab Evidence: Blood work showing immune-driven kidney irritation (glomerulonephritis). |
| Definite Diagnosis Rules | To confirm diagnosis, a patient must meet any of the following: • 2 major markers • 1 major + 3 minor markers • 5 separate minor markers |
The Modern Recovery Plan: Treating The Infection
Defeating a deep heart infection requires a fast-moving, coordinated medical team made up of cardiologists, infectious disease specialists, and heart surgeons.
Smarter Antibiotic Choices
The first line of defense is heavy-duty, targeted antibiotics. In the past, this meant keeping a patient hooked up to an IV line in a hospital bed for six weeks.
Today, updated medical protocols favor oral step-down antibiotic therapy for stable patients.
Once the initial, aggressive IV treatments bring the infection under control during the first two weeks, specific patients can safely switch to highly concentrated pills. As a result, they are allowed to finish the rest of their recovery comfortably at home.
When Surgery Is Required
Roughly half of all patients develop complications that medication alone cannot fix.
Emergency surgery becomes a necessity in case of the following:
- The infection is physically destroying the valve and causing acute heart failure
- The bacteria resist all available drugs
- A vegetation grows dangerously large, threatening an immediate stroke
The surgeon must completely cut away every trace of infected tissue and repair or replace the damaged valve.
Long-Term Outlook And Future Complications
Even after clearing the active infection, the structural changes left behind can create permanent, long-term health challenges.
- Leaky Heart Valves: The structural damage can leave valves permanently scarred and leaking, forcing the heart to work twice as hard and eventually leading to chronic heart failure.
- Traveling Clots: If pieces of a vegetation snap off early in the treatment process, they can travel up the main arteries, causing sudden ischemic strokes, sudden vision loss, or localized organ damage.
- Secondary Pockets: Escaping bacteria can seed secondary infections throughout the body, creating deep pockets of infection in the spine or brain that require separate, long-term care.
Awareness Saves Lives
Endocarditis remains a complex puzzle in modern cardiology, requiring a sharp eye for bacterial behavior and structural heart vulnerabilities.
Improving survival rates ultimately comes down to early action:
- recognizing subtle, fading symptoms
- using preventative antibiotics before dental work if you are at high risk
- bringing in a multi-disciplinary medical team the moment an infection threatens the heart
Moving past older, rigid clinical assumptions has allowed doctors to use better imaging and flexible oral therapies. As a result, doctors can better protect patient health.
Disclaimer: The information provided in this article is for general informational purposes only. It does not, and is not intended to, constitute medical or health advice. Please consult a qualified healthcare professional for medical guidance or expert health assistance.
Read Also: